

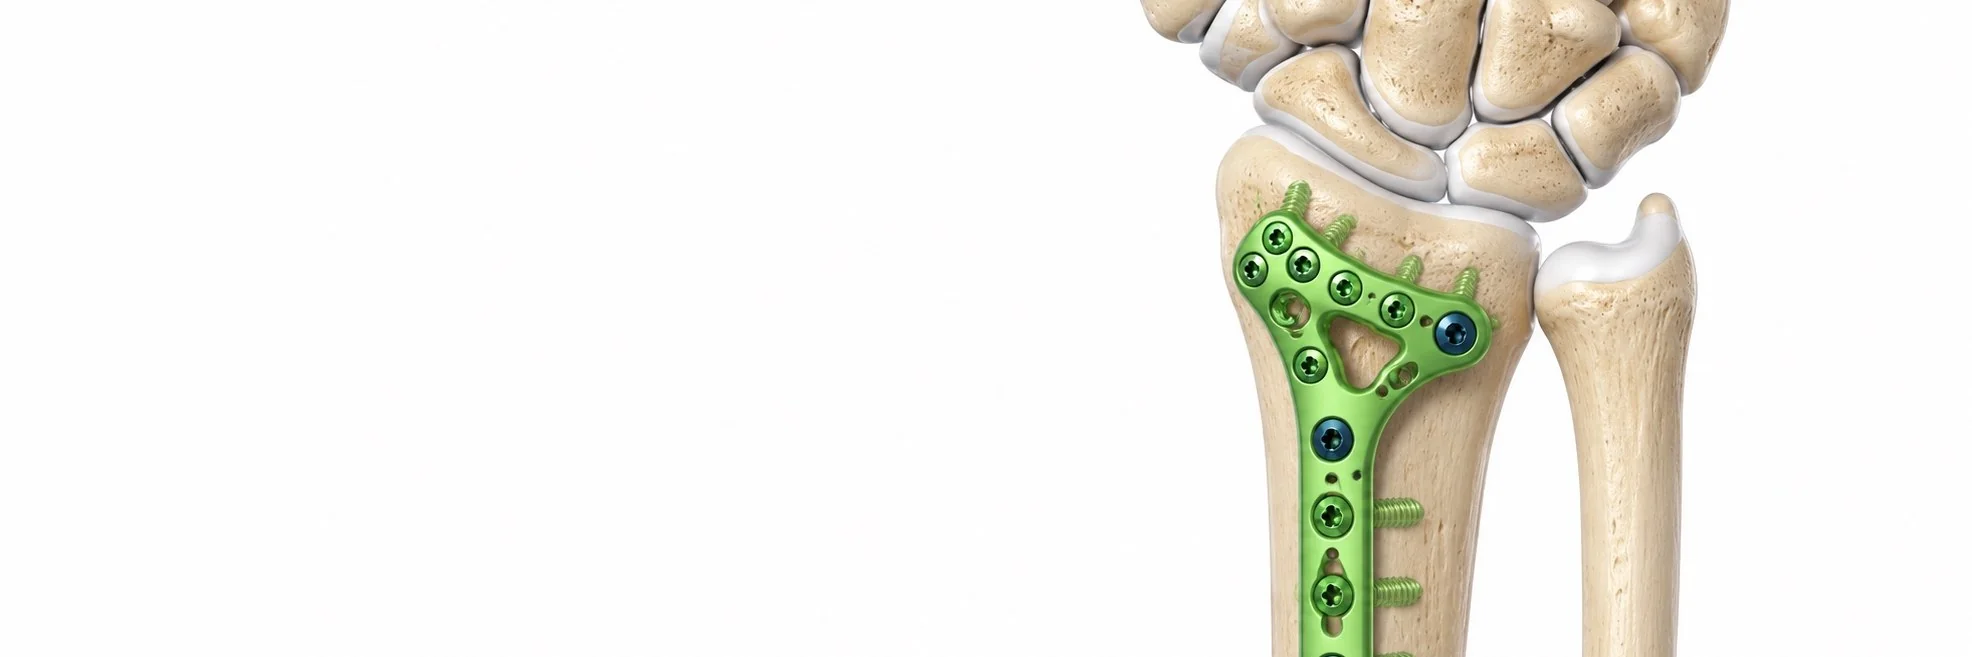
What does distal radius fixation involve?
Distal radius fixation is the surgical reconstruction of unstable or displaced fractures of the radius near the wrist. Modern techniques use a low-profile locking plate placed on the volar (palmar) side of the bone, providing stable fixation with minimal disturbance of the wrist tendons and soft tissues.
The volar locking plate has transformed wrist fracture surgery over the past 20 years, anatomical fixation, early mobilisation, and reliable restoration of function are now standard expectations.
When is fixation needed?
Operative fixation is recommended for:
- unstable fractures that redisplace or angulate following closed reduction
- displaced intra-articular fractures with joint surface step-off
- fractures with significant shortening of the radius (radial shortening with altered ulnar variance)
- open fractures or fractures with compression or compromise of the median nerve
I make a point of explaining that anatomical reduction matters. The distal radius supports the biomechanics of the entire wrist and hand, even small malunions translate into long-term wrist pain, weakness and stiffness, particularly in younger patients with many active years ahead.
How is the operation performed?
I perform distal radius fixation through a carefully planned incision on the volar side of the wrist (volar approach). The procedure includes:
- careful surgical exposure protecting the median nerve and the flexor tendons
- reduction of the fracture under direct vision and fluoroscopic guidance
- fixation using a low-profile volar locking plate, with screws supporting the joint surface
- when needed, additional fragment-specific fixation techniques for radial styloid or dorsal lunate facet fragments
- final fluoroscopic confirmation of anatomical reduction
I apply modern surgical techniques aiming for anatomical reconstruction of the joint surface, restoration of radial length, inclination, and alignment, and stable fixation that permits early mobilisation.
What should the patient expect after surgery?
- most procedures are performed as day-case surgery
- a removable splint is worn for 1–2 weeks, then removed for exercises
- gentle wrist mobilisation begins within the first postoperative week
- structured physiotherapy is essential to restore range of motion and grip strength
- driving usually resumes at 4–6 weeks
- most patients regain functional wrist mobility by 3 months
- return to heavier or demanding activities at 3–6 months depending on the fracture
What is the long-term outcome?
Outcomes following volar plate fixation are generally excellent:
- over 90% of patients regain functional wrist mobility and grip strength
- reliable maintenance of fracture reduction with low rates of late displacement
- most plates do not require long-term removal
I want to be clear that distal radius fixation, when performed with careful attention to anatomical reduction and preservation of the soft tissues, provides reliable long-term results.