

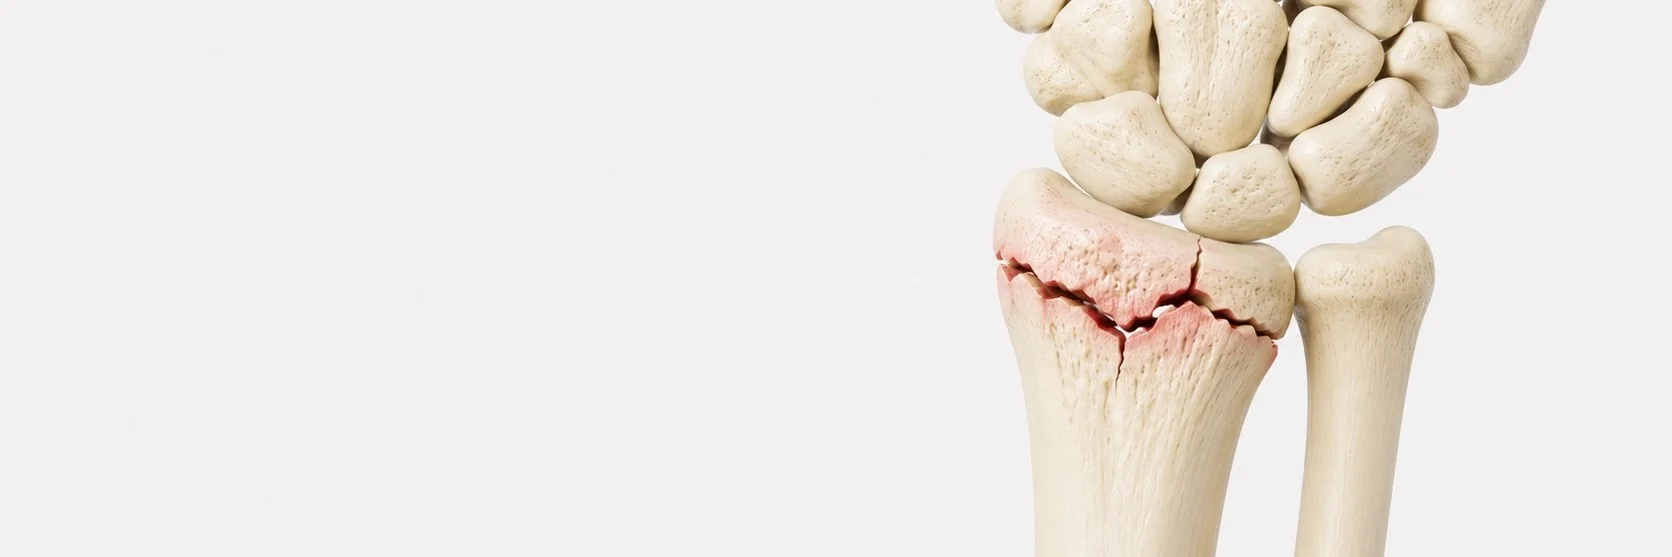
What is a distal radius fracture?
A distal radius fracture is a break of the radius bone near the wrist. It is the most common fracture in adults, occurring most often after a fall onto an outstretched hand.
Two patient groups are particularly affected: younger adults with high-energy injuries (falls from height, sport) and older patients with osteoporosis where even a low-energy fall can produce a fracture.
What are the symptoms?
- immediate pain and swelling at the wrist
- visible deformity in displaced fractures (the classic "dinner fork" deformity)
- inability to use the wrist or hand normally
- numbness or tingling in the fingers, possible nerve involvement requiring urgent assessment
How is it diagnosed?
- clinical examination focused on deformity, swelling and any nerve compromise
- X-rays in two views to confirm the fracture and assess displacement
- CT scan in selected complex intra-articular fractures for surgical planning
How is it treated?
Treatment depends on the fracture pattern, displacement and patient factors:
- stable, minimally displaced fractures, closed reduction and cast for 4–6 weeks
- unstable or displaced fractures, open reduction and internal fixation, typically with a volar locking plate
- severely comminuted or open fractures, external fixation, sometimes combined with limited internal fixation
It is worth being clear that anatomical reduction matters. Even small residual malalignments can produce significant long-term wrist pain and stiffness, particularly in young patients.
What is the recovery like?
- after surgical fixation, most patients begin gentle wrist motion within the first week
- after closed treatment, motion begins after cast removal at 4–6 weeks
- physiotherapy is essential to restore range of motion and grip strength
- most patients regain functional wrist motion by 3 months
- final recovery typically takes 6 months
I apply modern fixation techniques aiming for stable reconstruction that allows early motion, the key to restoring full wrist function.