


Often, yes. Many meniscus tears settle without an operation, particularly the degenerative tears that become common from middle age onwards. Whether a tear can be managed without surgery depends on what kind of tear it is, where it sits in the meniscus, the symptoms it causes and what you need your knee to do. A knee that locks is the main exception, and needs prompt assessment.
Key points
- Many meniscus tears do not need an operation. Whether yours does depends on the type of tear, its position and the symptoms it causes.
- Degenerative tears, which develop gradually from middle age onwards, are usually treated first with a structured exercise programme. In randomised trials, arthroscopic surgery did not give better results than exercise or a sham operation for these tears.
- Traumatic tears in younger, active people are different. Some can be repaired, and a repair is easier when it is done soon after the injury.
- A knee that is locked and cannot straighten, or keeps giving way, needs prompt assessment rather than a long wait.
- The aim of non-surgical treatment is a comfortable, strong knee. A tear that is still visible on a scan is not, on its own, a reason for surgery.
What the meniscus does
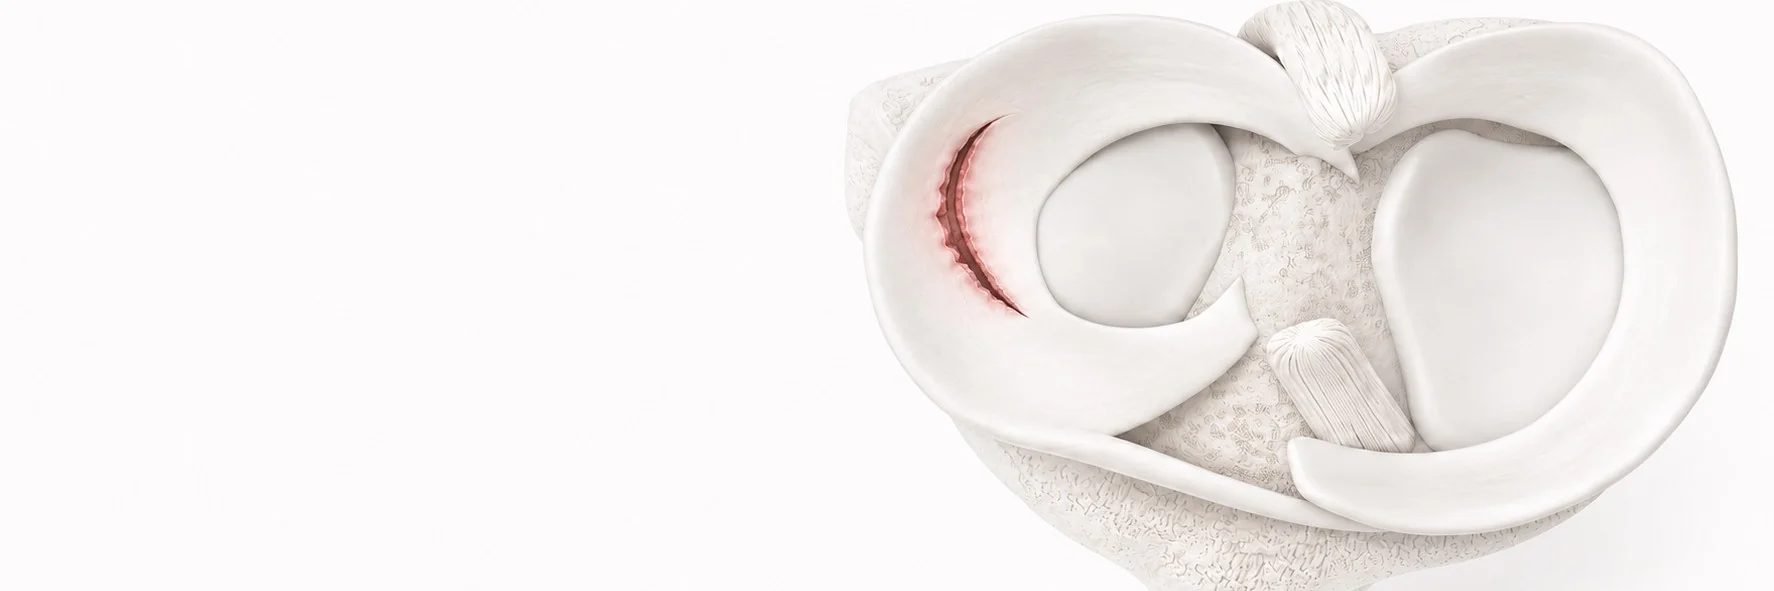
Each knee has two menisci, C-shaped cushions of cartilage between the thigh bone and the shin bone. They spread load across the joint and help keep it stable. Because they protect the joint, modern treatment aims to preserve as much meniscus as possible, whether or not surgery is needed.
Not all tears are the same
Two broad groups behave very differently.
Degenerative tears develop gradually as the meniscus tissue ages, usually from middle age onwards. They may follow a minor twist, or no clear injury at all. Pain along the joint line, often worse with squatting or twisting, is typical.
Traumatic tears happen with a clear injury, typically a twist with the foot planted, and are more common in younger, active people. They may come with other injuries, such as a torn anterior cruciate ligament.
Where the tear lies also matters. Only the outer edge of the meniscus, roughly the outer 10 to 25%, has a blood supply. Tears in that outer zone therefore have a better chance of healing, on their own or after a repair, than tears in the inner part.
Degenerative tears: exercise first
For degenerative tears without locking, the first step is a structured, supervised exercise programme. This approach is supported by randomised trials:
- In middle-aged patients with a degenerative tear, a supervised exercise programme gave results similar to arthroscopic partial meniscectomy two years later, and improved thigh-muscle strength more in the short term.
- In patients with a degenerative tear and no arthritis, partial meniscectomy gave results no better than a sham (placebo) operation at one year.
The European (ESSKA) consensus on degenerative meniscus lesions reached the same conclusion: arthroscopic partial meniscectomy should not be the first treatment, and surgery should be considered only after about three months without improvement, unless the knee has true mechanical symptoms such as locking.
This does not mean surgery never helps. It means that for most degenerative tears, exercise is the right place to start.
What "healing" means
When a degenerative tear "heals" without surgery, what usually happens is that the pain and swelling settle and the knee becomes strong and comfortable again. The tear may still be visible on a later scan. That is not, on its own, a reason for surgery: treatment is guided by how the knee feels and works, not by the picture alone.
Traumatic tears in younger, active people
Here the decision is more individual. A small, stable tear at the outer edge may settle with rehabilitation. Larger or unstable tears, tears that cause locking, and tears that occur together with an ACL injury are often better repaired. The European consensus on traumatic tears recommends preserving the meniscus whenever possible, because long-term results are worse after removing part of it, and doing a repair as early as possible when one is needed. That is why a younger patient with a fresh injury should be assessed early rather than wait many months.
What a non-surgical programme involves
- Easing the load for a while: reducing deep squatting, kneeling and twisting while the knee settles.
- Physiotherapy: progressive strengthening of the thigh and hip muscles, balance and movement control.
- Pain relief when needed, as advised by your doctor.
- Gradual return to activity, guided by how the knee responds rather than by a fixed date.
When waiting is not a good idea
- the knee is locked and you cannot straighten it fully
- you cannot put weight on the leg
- the knee keeps giving way, or swelled up quickly after an injury
- symptoms are getting worse despite rest and a structured programme
A locked knee can be a sign of a displaced tear (for example a "bucket-handle" tear) that is blocking the joint. This usually needs prompt arthroscopic surgery, and the chances of repairing the meniscus are better if it is treated early.
The bottom line
Many meniscus tears, especially degenerative ones, can be managed well without an operation. A clear diagnosis, an honest look at what the tear is doing and a proper exercise programme are the foundations. Surgery has an important place, particularly for locked knees and for repairable tears in younger patients, and the decision is best made together after an examination. More about the condition itself is in the meniscus tear guide. If you have also injured your ACL, see recovery after ACL reconstruction.
Frequently asked questions
Can I walk on a torn meniscus?
Usually, yes. Most people with a meniscus tear can walk, although twisting, squatting and kneeling may hurt. If the knee locks and will not straighten, or you cannot put weight on the leg, have it assessed promptly.
Do I need an MRI scan?
Not always straight away. A clinical examination often gives a good picture, and an MRI is useful when it will change the decision: for example in a younger patient after an injury, when the knee locks, or when symptoms do not improve with treatment. Meniscus tears are common on scans of people without symptoms (in one large study, most people found to have a tear had had no knee pain in the previous month), so a scan is always read together with the examination.
How long should I try physiotherapy before considering surgery?
For a degenerative tear without locking, European consensus advises about three months of non-surgical treatment before an operation is considered. If the knee is clearly improving, you continue. If it is not, or it starts to lock, the options are reviewed again.
Will the tear get worse if I don't have surgery?
Not necessarily. Many degenerative tears stay stable and the symptoms settle. What matters is how the knee behaves: new locking, repeated swelling or giving way are reasons to be reassessed.
Can I keep playing football or padel with a meniscus tear?
Sports with twisting and sudden stops load the meniscus heavily. Until the knee has been assessed and is no longer painful or swollen, it is wise to pause them and keep active with cycling or swimming instead.
References
- Kise NJ, Risberg MA, Stensrud S, Ranstam J, Engebretsen L, Roos EM. Exercise therapy versus arthroscopic partial meniscectomy for degenerative meniscal tear in middle aged patients: randomised controlled trial with two year follow-up. BMJ 2016;354:i3740. doi:10.1136/bmj.i3740 · PubMed 27440192
- Sihvonen R, Paavola M, Malmivaara A, Itälä A, Joukainen A, Nurmi H, Kalske J, Järvinen TLN. Arthroscopic Partial Meniscectomy versus Sham Surgery for a Degenerative Meniscal Tear. N Engl J Med 2013;369(26):2515-2524. doi:10.1056/NEJMoa1305189 · PubMed 24369076
- Beaufils P, Becker R, Kopf S, Englund M, Verdonk R, Ollivier M, et al. Surgical management of degenerative meniscus lesions: the 2016 ESSKA meniscus consensus. Knee Surg Sports Traumatol Arthrosc 2017;25(2):335-346. doi:10.1007/s00167-016-4407-4
- Kopf S, Beaufils P, Hirschmann MT, Rotigliano N, Ollivier M, Pereira H, et al. Management of traumatic meniscus tears: the 2019 ESSKA meniscus consensus. Knee Surg Sports Traumatol Arthrosc 2020;28(4):1177-1194. doi:10.1007/s00167-020-05847-3
- Englund M, Guermazi A, Gale D, Hunter DJ, Aliabadi P, Clancy M, Felson DT. Incidental Meniscal Findings on Knee MRI in Middle-Aged and Elderly Persons. N Engl J Med 2008;359(11):1108-1115. doi:10.1056/NEJMoa0800777 · PubMed 18784100
- Arnoczky SP, Warren RF. Microvasculature of the human meniscus. Am J Sports Med 1982;10(2):90-95. doi:10.1177/036354658201000205
This article is general patient information. It does not replace an individual medical assessment, diagnosis or treatment. If you have symptoms, please see a doctor.